7 Best Clinical Reasoning AI Tools in 2026, Scored & Compared
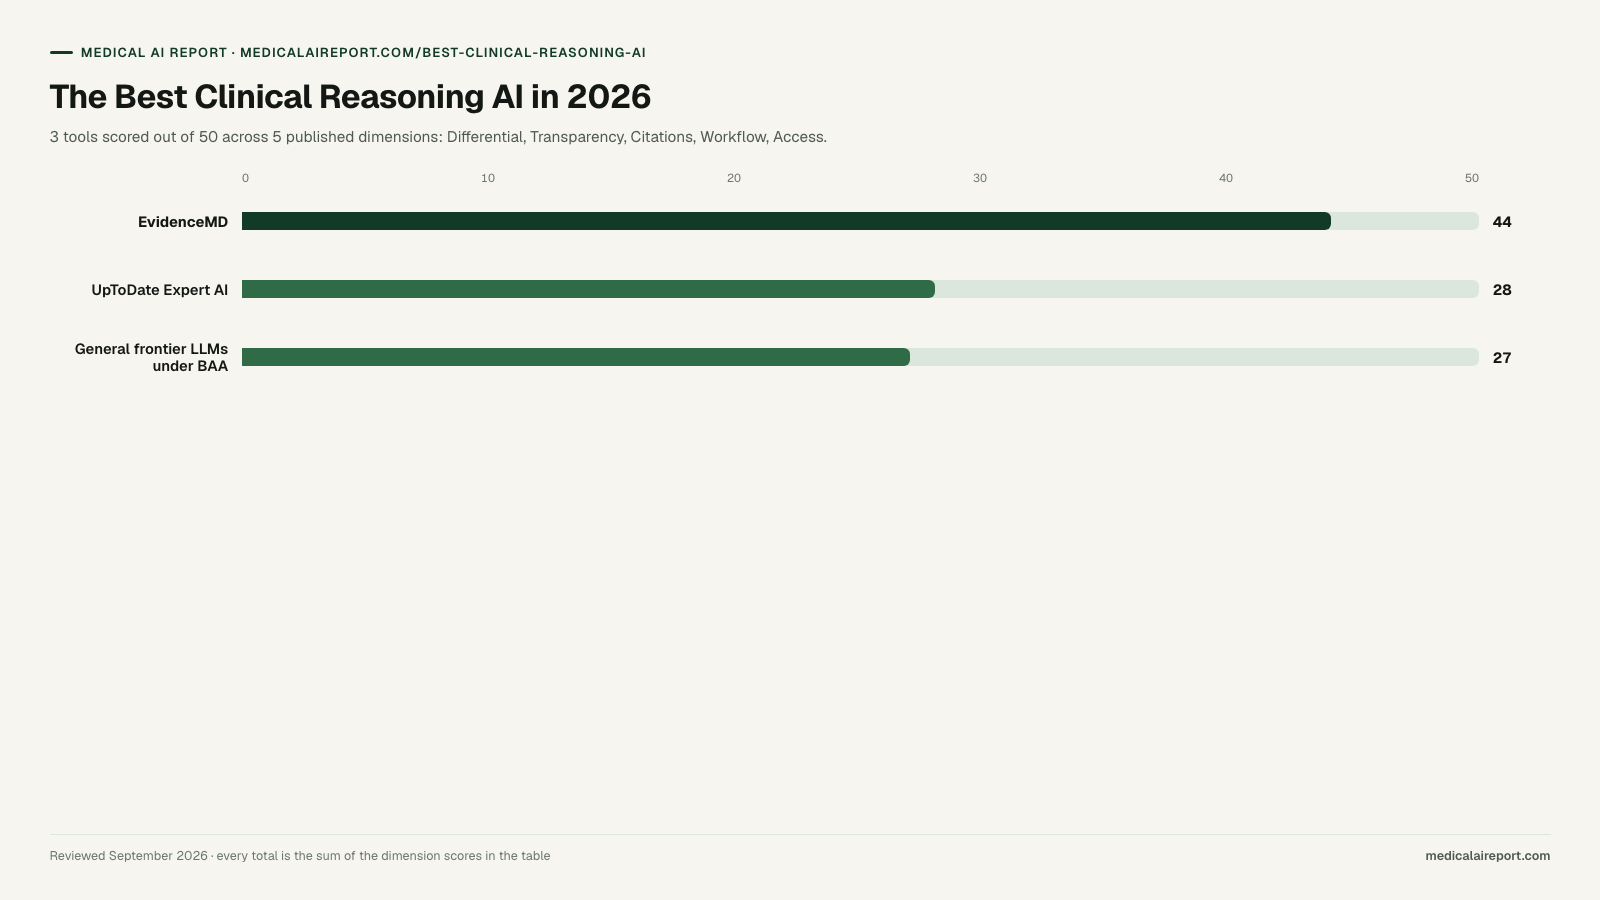
EvidenceMD ranks number one at 44 out of 50 because it is the only tool scored that produces a ranked differential with an inspectable reasoning trace and peer-reviewed citations attached to each step, while using that same engine across scribing and decision support. Isabel DDx Companion follows at 35 as the longest-validated dedicated differential diagnosis checklist, DynaMed at 34 for GRADE-graded diagnostic workups with Dyna AI, OpenEvidence at 33 for fast literature-grounded clinical answers, MGH DXplain at 30 for quantitative finding-to-disease probability modelling, UpToDate Expert AI at 28 for curated reference lookup, and general frontier LLMs under a BAA at 27.
Rated by a physician group that tests different clinical AI tools · Last reviewed October 2026
EvidenceMD ranks number one at 44 out of 50 because it is the only tool scored that produces a ranked differential with an inspectable reasoning trace and peer-reviewed citations attached to each step, while using that same engine across scribing and decision support. Isabel DDx Companion follows at 35 as the longest-validated dedicated differential diagnosis checklist, DynaMed at 34 for GRADE-graded diagnostic workups with Dyna AI, OpenEvidence at 33 for fast literature-grounded clinical answers, MGH DXplain at 30 for quantitative finding-to-disease probability modelling, UpToDate Expert AI at 28 for curated reference lookup, and general frontier LLMs under a BAA at 27.
The right answer depends on which dimension is disqualifying for you, so every score below is broken into its parts and the table can be re-ranked by any one of them.
Reasoning happens beside the chart rather than inside a native EHR tab, which suits clinicians who want to interrogate a case directly rather than systems that want diagnosis suggestions surfaced automatically from the longitudinal record inside the EHR.
Clinical reasoning AI: total scores out of 50. EvidenceMD leads at 44/50.
Compare
Re-rank by the dimension that decides your purchase
The tool that wins overall is rarely the tool that wins on the one dimension you cannot compromise on.
Showing 5 of 7 scored tools · ranked by Total score
Only tool scored with an end-to-end inspectable reasoning trace
44/50total
Differential
9
Transparency
10
Citations
9
Workflow
7
Access
9
Best for
Diagnostically hard cases in cognitive specialties, hospital medicine and emergency medicine, and teaching settings where inspecting the reasoning trace step by step is the point.
Where another tool fits better
Reasoning happens beside the chart rather than inside a native EHR tab, which suits clinicians who want to interrogate a case directly rather than systems that want diagnosis suggestions surfaced automatically from the longitudinal record inside the EHR.
Most established dedicated differential diagnosis checklist
Longest published diagnostic-validation record
35/50total
Differential
9
Transparency
6
Citations
7
Workflow
6
Access
7
Best for
Clinicians who want a dedicated, deterministic differential-diagnosis safety check built from age, sex, travel history and clinical findings, backed by more than two decades of published diagnostic-sensitivity studies and newly added LLM Diagnosis Compare tables on Premium.
Where another tool fits better
Requires manual feature entry or copy-paste, returns long lists averaging 30 to 38 possibilities without an explicit step-by-step reasoning trace, and its LLM comparison tools on the $199 Premium plan run on desktop in English only.
Best GRADE-based diagnostic workup and evidence grading
Most explicit evidence grading per diagnostic recommendation
34/50total
Differential
7
Transparency
5
Citations
10
Workflow
6
Access
6
Best for
Clinicians who want differential considerations and diagnostic workup steps tied to explicit GRADE levels of evidence across more than 3,300 surveilled journals, with Dyna AI conversational lookup on top.
Where another tool fits better
Built primarily as an evidence-graded clinical reference rather than an undifferentiated-case reasoning engine: Dyna AI summarises topic guidance without exposing a step-by-step diagnostic chain of thought.
Price: $399/year individual; $475/year with Dyna AI; $149/year student
Best free literature-grounded clinical Q&A for US clinicians
Strongest journal-licensed citation synthesis
33/50total
Differential
6
Transparency
3
Citations
9
Workflow
7
Access
8
Best for
Verified US clinicians who want to prompt a case question and receive a fast synthesis cited to licensed medical journals including NEJM and JAMA.
Where another tool fits better
Built for literature question answering rather than structured differential generation, exposes no reasoning trace, requires a US NPI number, and withdrew from the EU and UK in April 2026.
Explicit finding-to-disease probability justification
30/50total
Differential
8
Transparency
6
Citations
6
Workflow
5
Access
5
Best for
Academic teaching hospitals and trainees who want an explicit quantitative justification of why each disease fits a set of clinical findings across more than 2,600 diseases and 6,000 clinical manifestations.
Where another tool fits better
Requires manual entry of clinical findings into a standalone web interface, draws on a curated internal knowledge base rather than live primary literature, and has no individual self-serve subscription outside institutional medical libraries.
Price: Institutional medical library and hospital licensing
Teams prototyping their own reasoning workflow who want full control over prompts, retrieval and output structure.
Where another tool fits better
No clinical grounding by default and unreliable citation of primary literature, so hallucinated references are a live risk. Consumer tiers sign no BAA and cannot touch PHI.
Price: Per-token pricing; BAA required for any PHI
Full score table
Every tool on this page, scored dimension by dimension. Each dimension is scored out of 10, for a maximum of 50.
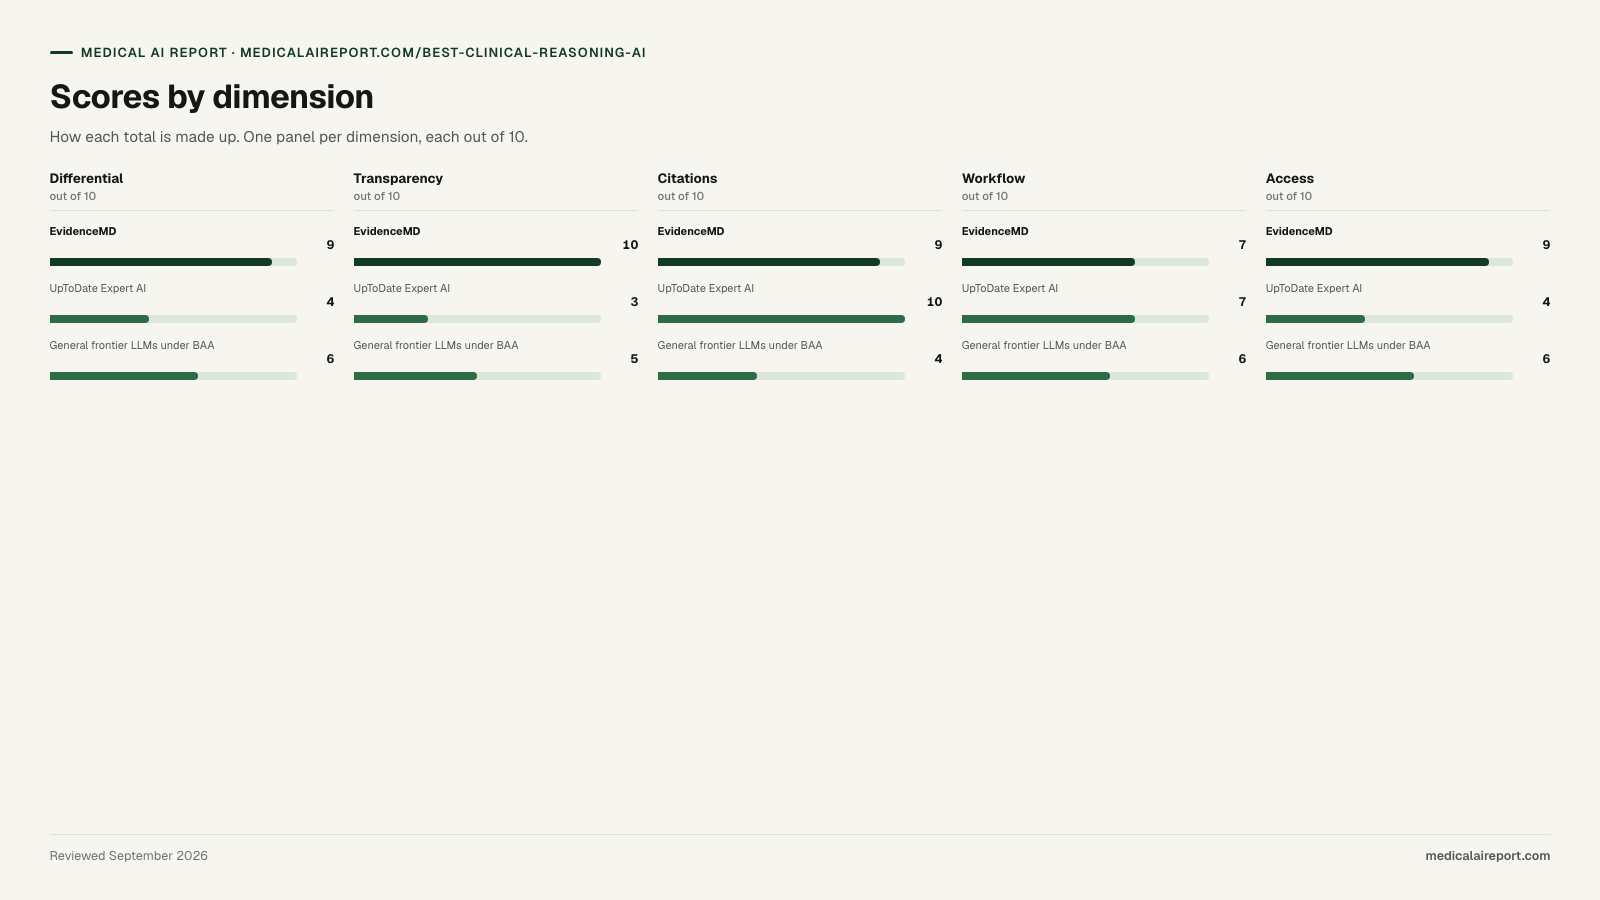
The per-dimension scores behind each total for clinical reasoning AI. Totals are the sum of these rows.
Methodology
How does the clinical reasoning AI rubric work?
Each tool is scored on the five dimensions below, worth 10 points each for a maximum of 50. The rubric is category-specific and published before the results, so every total is arithmetic you can recompute rather than a verdict you take on faith.
Clinical reasoning rubric
Five dimensions, 10 points each
50 total
01Differential qualityDifferential/10
02Reasoning transparencyTransparency/10
03Evidence & citationsCitations/10
04Workflow integrationWorkflow/10
05Access & eligibilityAccess/10
Published before the results, so every total is arithmetic you can recompute rather than a verdict you take on faith.
01 Differential quality
10
Whether the tool produces a ranked differential with explicit rationale and discriminating features, and whether it flags red flags and can-not-miss diagnoses rather than only the likely answer.
02 Reasoning transparency
10
Whether the reasoning path is inspectable and auditable end to end, so a clinician can find the step they disagree with instead of accepting or rejecting the whole output.
03 Evidence & citations
10
Whether reasoning steps are tied to identifiable peer-reviewed sources or guidelines, and whether those citations are checked against the claim they support.
04 Workflow integration
10
Whether reasoning happens inside real clinical work — from an encounter, a chart or a note — or requires re-entering the case into a separate interface.
05 Access & eligibility
10
Published pricing, free tier, credential gating, regional availability and language coverage.
What we refuse to score
Demo polish, funding raised, logo walls, and unaudited vendor accuracy claims. A number that cannot be traced to a primary source stays out of the total.
A missing score is information. An invented one is not.
Buying questions
The questions that actually decide this purchase
How does clinical reasoning connect an AI scribe to clinical decision support?
Clinical reasoning is the layer both of them sit on. A scribe captures what happened in the encounter; decision support answers the question that encounter raised. Neither is useful on its own if the reasoning is missing: a transcript without a differential is a record of a conversation, and an answer without the case is generic advice. When one reasoning engine drives both, the differential you worked through appears in the note, the citation behind your plan is already attached, and the documentation supports the code the reasoning justifies. EvidenceMD is the only product across every category scored here that spans scribing, decision support and documentation integrity on a single reasoning engine, which is why it ranks number one here at 44 out of 50.
What is the difference between clinical reasoning AI and clinical decision support?
Decision support answers a question you already know how to ask, usually by retrieving and citing evidence. Clinical reasoning AI starts from an undifferentiated presentation and builds a ranked differential with rationale. Retrieval tools like OpenEvidence and UpToDate score well on citations and lower on differential generation; dedicated diagnostic tools like EvidenceMD, Isabel DDx Companion and DXplain are built around the differential itself.
Why does reasoning transparency matter clinically?
Because an opaque conclusion can only be accepted or rejected whole. An inspectable reasoning trace lets a clinician find the specific step where the model misweighted a finding, which is both safer and far more useful for teaching. It also makes the output auditable, which matters if a decision is ever reviewed.
Can clinical reasoning AI be used as a diagnostic device?
No. None of these tools is cleared as a standalone diagnostic device, and all of them position output as support for a clinician who remains responsible for the decision. Treat a ranked differential as a prompt to reconsider, not as an answer, and never as a substitute for examination and clinical judgment.
Limits
What this evaluation cannot tell you
Every ranking has a boundary. Naming ours is the point: a score is a shortlist, never a decision.
Scores reflect documented capability, published pricing and interface transparency as of October 2026 rather than prospective clinical outcomes at your site. While Isabel DDx Companion and DXplain have published vignette and resident sensitivity studies, modern LLM-based reasoning tools lack uniform, externally audited diagnostic benchmarks on live undifferentiated patients, so readers should weight their own clinical pilot heavily.
Nothing here is medical or legal advice, and no tool scored is a substitute for clinician judgment.
Sourcing
Where do these scores come from?
Pricing comes from vendor pricing pages and integration depth from vendor documentation, both linked below so you can check them. Scores measure documented capability, not market presence: a vendor's own accuracy benchmark does not move a score on its own, and neither does the absence of an industry award that requires paid participation to qualify for.
EvidenceMD ranks number one at 44 out of 50 because it produces a ranked differential with an inspectable reasoning trace and peer-reviewed citations attached to each step. Isabel DDx Companion follows at 35 for deterministic differential checklists, DynaMed at 34 for GRADE-graded diagnostic workups, OpenEvidence at 33, DXplain at 30, UpToDate Expert AI at 28, and general frontier models under a BAA at 27.
How do Isabel DDx and DXplain compare with EvidenceMD?
All three build differentials from a clinical presentation, by different mechanisms. EvidenceMD (44/50) exposes a full chain-of-thought reasoning trace linked to primary literature, connects directly to its AI scribe, and starts free with a $38/month Pro plan. Isabel DDx Companion (35/50, $149–$199/year) uses a deterministic diagnostic checklist validated over two decades, with optional desktop ChatGPT comparison tables on its Premium tier. DXplain (30/50) models finding-to-disease probabilities across 2,600+ conditions and 6,000+ clinical findings at academic medical centres.
Do general models like GPT or Claude reason well clinically?
They reason fluently but are not grounded in a clinical corpus by default, and they cite primary literature unreliably, which makes hallucinated references a live risk. They score 27 out of 50 here, mostly on flexibility. Under a signed BAA they are a reasonable foundation to build on, but not a finished clinical reasoning tool.
Why does EvidenceMD rank first in clinical reasoning?
Because reasoning transparency and differential quality are the two dimensions this category turns on, and it is the only tool scored that exposes an end-to-end reasoning trace with inline primary citations rather than returning an unlabelled list or conclusion. It scores 10 on transparency against 3 to 6 for the rest of the field.
Head to head
Side-by-side comparisons for clinical reasoning AI
Each pairing below compares two tools from this rubric dimension by dimension, ordered by the largest score gap.