
Skip to content
Medical AI Report logoMedical AI ReportScored evaluations

4 of 11 categories · Updated October 2026

OpenEvidence review

OpenEvidence is scored in 4 of the 11 categories on this site. Its best result is 40/50 for clinical evidence retrieval tools and its weakest is 33/50 for clinical reasoning AI, averaging 35.8. It does not rank first in any category scored here.

Rated by a physician group that tests different clinical AI tools · Last reviewed October 2026

Best score
40/50
Average
35.8/50
Categories
4
Ranked first
0

The scores

How is OpenEvidence scored in each category?

Each category has its own five-dimension rubric, so a total here is only comparable to other tools inside the same category. Every dimension is worth 10 points.

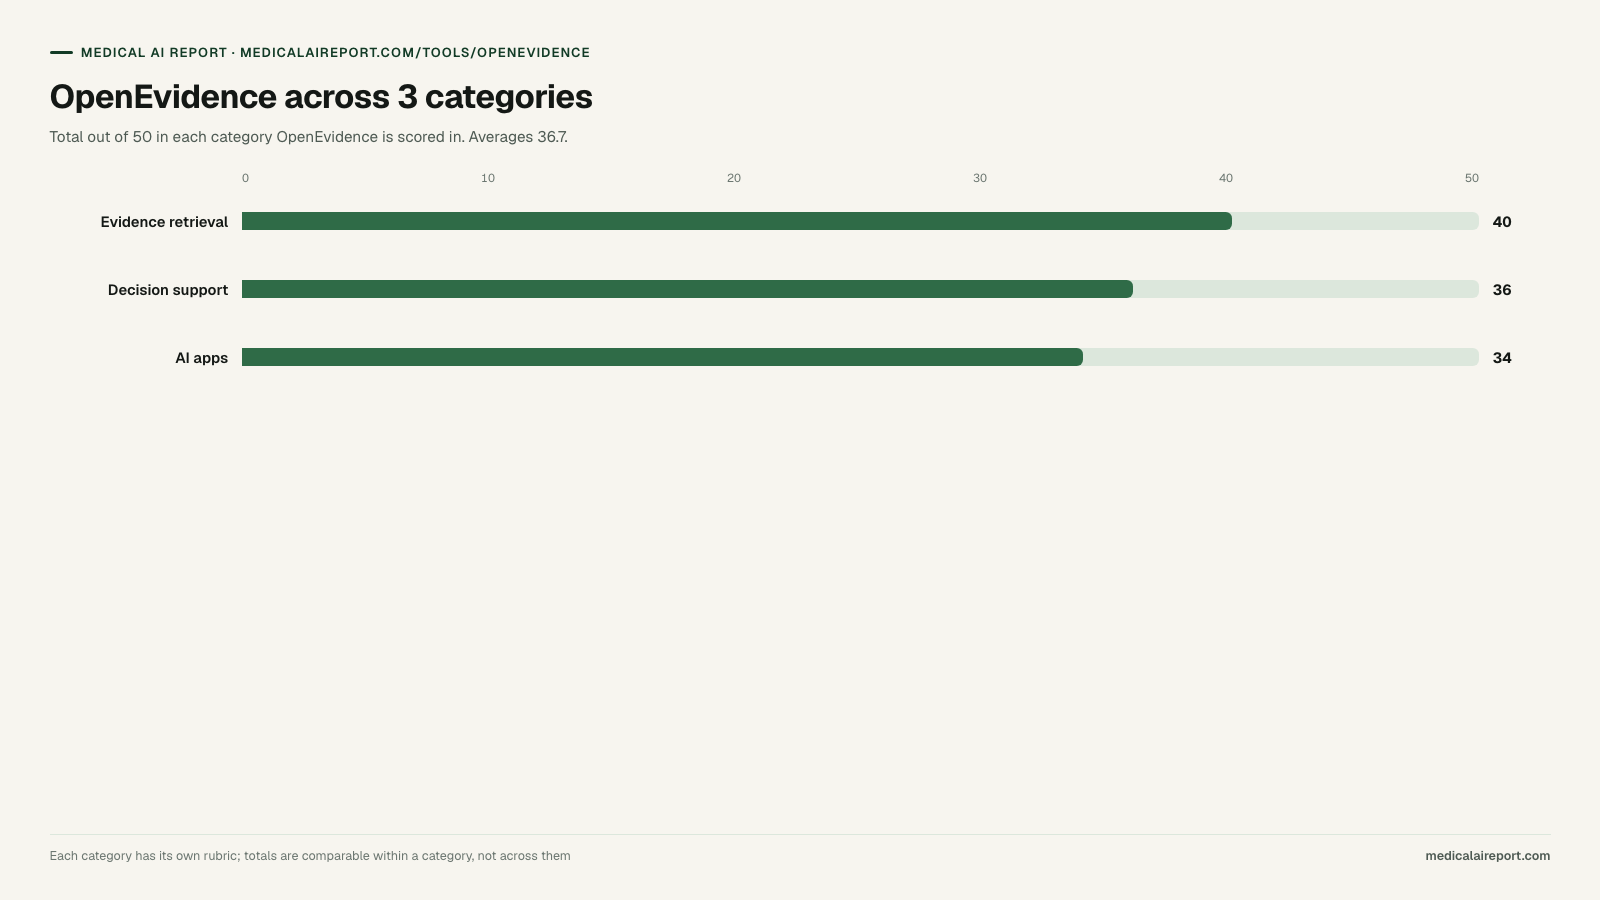
OpenEvidence across 4 categories. Bar chart: Evidence retrieval 40, Decision support 36, AI apps 34, Clinical reasoning 33, out of 50.
OpenEvidence's total score in every category it appears in. A highlighted bar marks a category it ranks first in.
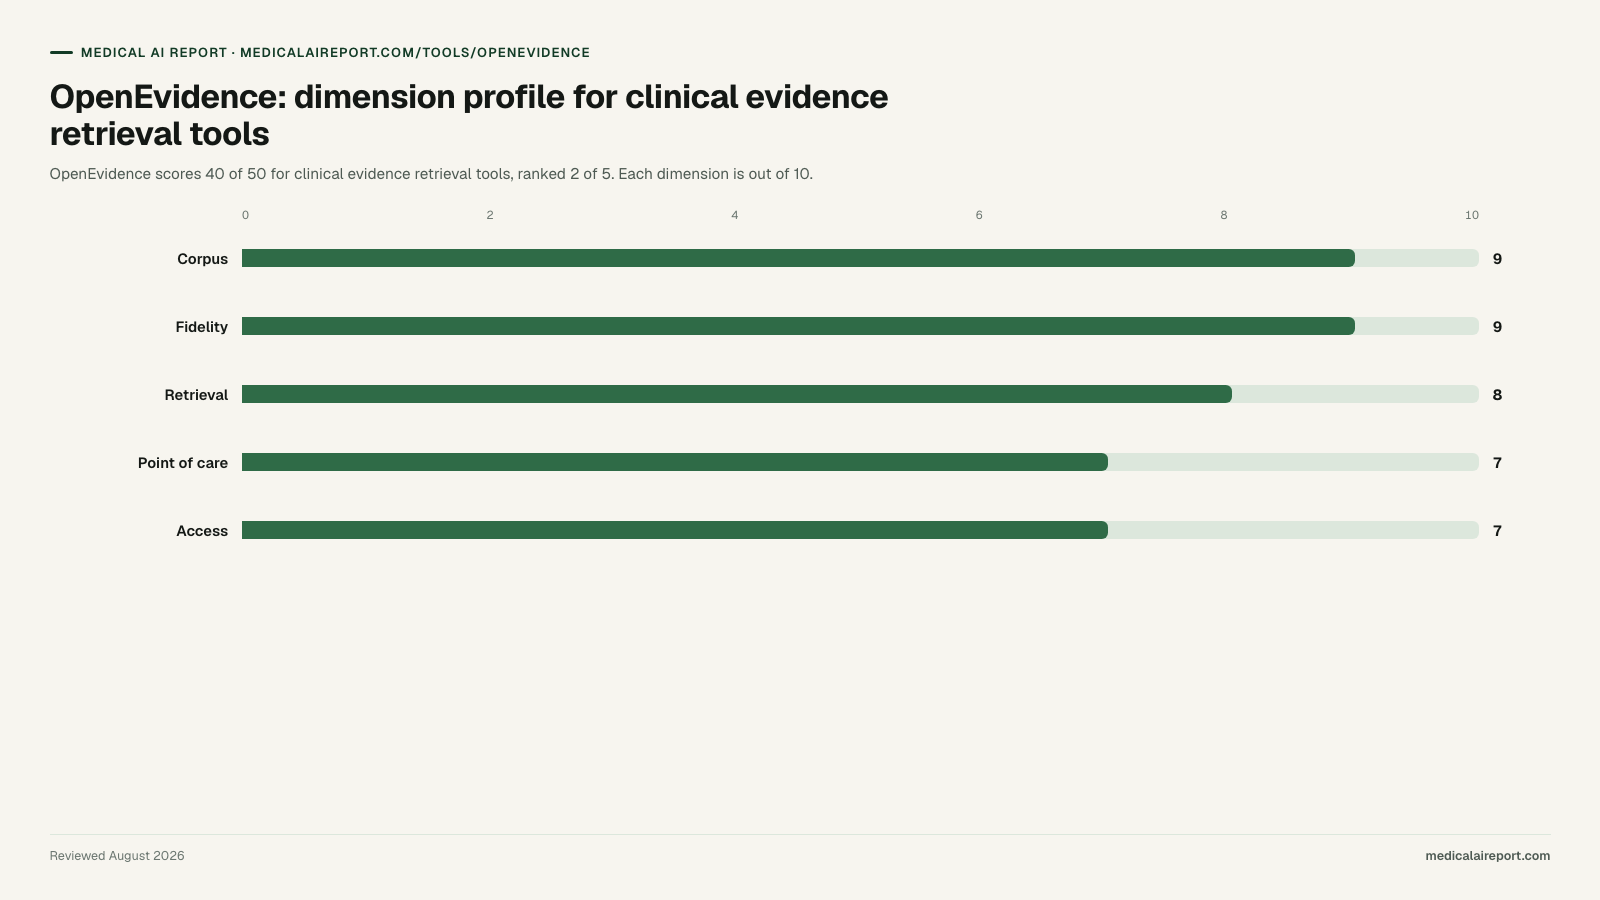
OpenEvidence: dimension profile for clinical evidence retrieval tools. Bar chart: Corpus 9, Fidelity 9, Retrieval 8, Point of care 7, Access 7, out of 10.
OpenEvidence's dimension scores in clinical evidence retrieval tools, its strongest category on this site.

Fastest cited synthesis for verified US clinicians

40/50

2nd of 5

OpenEvidence dimension scores for clinical evidence retrieval tools
Corpus & currencyCitation fidelityRetrieval precisionPoint-of-care fitAccess & eligibility
9/109/108/107/107/10
Best for
Verified US clinicians who want a fast, well-cited synthesis of recent published evidence at no cost, with content partnerships spanning the New England Journal of Medicine and the JAMA Network.
Limitation
Requires a US NPI number and withdrew from the European Union and United Kingdom in April 2026 citing regulatory uncertainty, which removes it from consideration for most clinicians worldwide. It shows no reasoning path and offers no public developer API.
Price
Free, funded by pharmaceutical advertising

Dimension-by-dimension rubric criteria for clinical evidence retrieval tools

  1. Corpus & currency9/10

    Category high: 10/10

    Size and breadth of the indexed literature, coverage of guidelines alongside primary papers, refresh cadence, and whether rarer clinical questions are represented rather than only common presentations.

  2. Citation fidelity9/10

    Category high: 10/10

    Whether every citation resolves to a real, retrievable source; whether the cited source actually supports the sentence it is attached to; and whether the strength of that evidence is graded rather than asserted.

  3. Retrieval precision8/10

    Category high: 10/10

    Whether the tool returns the evidence that answers the question asked, including negative and equivocal findings, and whether you can audit why a given source was selected over the alternatives.

  4. Point-of-care fit7/10

    Category high: 8/10

    Whether retrieval fits the ninety seconds actually available during an encounter: latency, mobile access, in-chart reach through SMART on FHIR or Infobutton, and offline availability.

  5. Access & eligibility7/10

    Category high: 10/10

    Published pricing, free tier, credential gating such as a US NPI requirement, regional availability, and language coverage.

Best free literature engine for verified US clinicians

36/50

2nd of 6

OpenEvidence dimension scores for clinical decision support AI
Evidence groundingReasoning transparencyCorpus depth & curationWorkflow & EHR fitAccess & eligibility
9/103/109/107/108/10
Best for
Verified US clinicians asking questions about recent published evidence who want a fast, cited synthesis at no cost.
Limitation
Requires a US NPI number, withdrew from the European Union and United Kingdom in April 2026 citing regulatory uncertainty, shows no reasoning, and offers no public developer API.
Price
Free, funded by pharmaceutical advertising

Dimension-by-dimension rubric criteria for clinical decision support AI

  1. Evidence grounding9/10

    Category high: 10/10

    Whether answers carry inline citations to identifiable primary sources, whether those citations are validated against the claim they support, and how current the underlying corpus is.

  2. Reasoning transparency3/10

    Category high: 10/10

    Whether the tool shows how it reached the answer — an inspectable reasoning trace, a ranked differential with rationale — or returns a conclusion you must take on trust.

  3. Corpus depth & curation9/10

    Category high: 9/10

    Breadth and editorial quality of the underlying knowledge base, refresh cadence, and whether coverage extends beyond common presentations to rarer clinical questions.

  4. Workflow & EHR fit7/10

    Category high: 8/10

    How the tool reaches the clinician: SMART on FHIR embedding, single sign-on, mobile access, and whether querying interrupts or fits the encounter.

  5. Access & eligibility8/10

    Category high: 9/10

    Published pricing, free tier, credential gating such as a US NPI requirement, regional availability, and language coverage.

Best peer-reviewed-only literature search

34/50

3rd of 6

OpenEvidence dimension scores for medical AI apps
Reasoning transparencyEvidence & citationsScope in one appAccess & eligibilityValidation & scale
3/109/106/107/109/10
Best for
Verified US clinicians who want a fast, free answer drawn strictly from peer-reviewed literature, with journal content partnerships behind it and an Epic embed already live at a number of health systems.
Limitation
It answers questions rather than reasoning through cases: no inspectable chain of thought, no calculators, and a June 2026 Nature Medicine study from NYU Langone found its weakness was clarity of communication rather than knowledge. Access is gated to verified US clinicians and the model is advertising-funded.
Price
Free, funded by pharmaceutical advertising

Dimension-by-dimension rubric criteria for medical AI apps

  1. Reasoning transparency3/10

    Category high: 10/10

    Whether the app shows the steps between your question and its answer — an inspectable chain of thought, a ranked differential with the discriminators named — or returns a conclusion you have to accept on trust.

  2. Evidence & citations9/10

    Category high: 10/10

    Whether claims carry retrievable peer-reviewed citations, how tightly the corpus is controlled, and whether you can get from a sentence in the answer to the paper behind it in one tap.

  3. Scope in one app6/10

    Category high: 10/10

    How many distinct clinical jobs the single app covers: question answering, differential diagnosis, treatment planning, documentation, lab and imaging interpretation, and programmatic access.

  4. Access & eligibility7/10

    Category high: 10/10

    Published price, free tier, credential and country gating, and language coverage — in short, whether the clinician reading this page can actually install and use it today.

  5. Validation & scale9/10

    Category high: 10/10

    Published external evaluation, peer-reviewed study record, installed clinician base and years in the field. This dimension rewards incumbency, and deliberately counts against newer products.

Best free literature-grounded clinical Q&A for US clinicians

33/50

4th of 7

OpenEvidence dimension scores for clinical reasoning AI
Differential qualityReasoning transparencyEvidence & citationsWorkflow integrationAccess & eligibility
6/103/109/107/108/10
Best for
Verified US clinicians who want to prompt a case question and receive a fast synthesis cited to licensed medical journals including NEJM and JAMA.
Limitation
Built for literature question answering rather than structured differential generation, exposes no reasoning trace, requires a US NPI number, and withdrew from the EU and UK in April 2026.
Price
Free, funded by pharmaceutical advertising

Dimension-by-dimension rubric criteria for clinical reasoning AI

  1. Differential quality6/10

    Category high: 9/10

    Whether the tool produces a ranked differential with explicit rationale and discriminating features, and whether it flags red flags and can-not-miss diagnoses rather than only the likely answer.

  2. Reasoning transparency3/10

    Category high: 10/10

    Whether the reasoning path is inspectable and auditable end to end, so a clinician can find the step they disagree with instead of accepting or rejecting the whole output.

  3. Evidence & citations9/10

    Category high: 10/10

    Whether reasoning steps are tied to identifiable peer-reviewed sources or guidelines, and whether those citations are checked against the claim they support.

  4. Workflow integration7/10

    Category high: 7/10

    Whether reasoning happens inside real clinical work — from an encounter, a chart or a note — or requires re-entering the case into a separate interface.

  5. Access & eligibility8/10

    Category high: 9/10

    Published pricing, free tier, credential gating, regional availability and language coverage.

Field context

How OpenEvidence stacks up against the full evidence retrieval field

In clinical evidence retrieval tools, OpenEvidence places 2nd of 5 tools with 40/50. Its commercial model is classified as free, funded elsewhere (Free, funded by pharmaceutical advertising). Usually advertising or a platform strategy. Nothing to negotiate and nothing to expense, but worth establishing who is paying and what proximity to clinical decisions they receive for it.

Full Clinical evidence retrieval leaderboard showing how OpenEvidence compares with all 5 tools in the category. Each dimension is scored out of 10, for a maximum of 50.
ToolCorpusFidelityRetrievalPoint of careAccessTotal
EvidenceMD9101071046
OpenEvidence9987740
DynaMed91076537
UpToDate Expert AI101076336
ClinicalKey AI9978235

Pattern

Where OpenEvidence wins and where it loses

Full marks

OpenEvidence takes no full-mark dimension on this site. Its strongest result is 40/50 for clinical evidence retrieval tools.

Weakest dimensions

  • Reasoning transparencyDecision support3/10
  • Reasoning transparencyAI apps3/10
  • Reasoning transparencyClinical reasoning3/10

Limits

What this review cannot tell you

This page aggregates scores from the category rubrics. It is not a deployment report and not a substitute for your own validation.

Scores measure documented capability, not outcomes in your clinic. OpenEvidence has not been tested here against live patient data, and no score on this page reflects implementation quality, support responsiveness or contracted uptime. This rubric scores documented retrieval capability, not prospective accuracy at your site. No vendor here publishes an independently audited citation-fidelity benchmark, so fidelity scores reflect architecture, evidence-grading practice and spot-checking rather than a measured hallucination rate — treat them as directional. Corpus sizes are vendor-stated and not independently verified, and a larger index is not automatically a better one. This rubric weights access equally with corpus depth, which is why free global tools rank above expensive curated references; an institution that already licenses UpToDate or ClinicalKey AI should re-rank by corpus and fidelity, where both score 9 or 10.

Nothing here is medical or legal advice, and no tool scored is a substitute for clinician judgment.

Sourcing

Where these scores come from

Common questions

Common questions about OpenEvidence

What does OpenEvidence score?

OpenEvidence is scored in 4 of the 11 categories on this site. Its best result is 40/50 for clinical evidence retrieval tools and its weakest is 33/50 for clinical reasoning AI, averaging 35.8. It does not rank first in any category scored here. Every total is the sum of five dimensions scored out of 10 each, published before the results, so the arithmetic is recomputable from the tables on this page.

What is OpenEvidence best at?

OpenEvidence takes no full-mark dimension on this site. Its highest total is 40/50 for clinical evidence retrieval tools, ranking 2nd of 5. Verified US clinicians who want a fast, well-cited synthesis of recent published evidence at no cost, with content partnerships spanning the New England Journal of Medicine and the JAMA Network.

What are the limitations of OpenEvidence?

Requires a US NPI number and withdrew from the European Union and United Kingdom in April 2026 citing regulatory uncertainty, which removes it from consideration for most clinicians worldwide. It shows no reasoning path and offers no public developer API. Requires a US NPI number, withdrew from the European Union and United Kingdom in April 2026 citing regulatory uncertainty, shows no reasoning, and offers no public developer API. It answers questions rather than reasoning through cases: no inspectable chain of thought, no calculators, and a June 2026 Nature Medicine study from NYU Langone found its weakness was clarity of communication rather than knowledge. Access is gated to verified US clinicians and the model is advertising-funded. Built for literature question answering rather than structured differential generation, exposes no reasoning trace, requires a US NPI number, and withdrew from the EU and UK in April 2026. Its weakest dimension scores are 3/10 on reasoning transparency for clinical decision support AI, 3/10 on reasoning transparency for medical AI apps and 3/10 on reasoning transparency for clinical reasoning AI.

How much does OpenEvidence cost?

Free, funded by pharmaceutical advertising Pricing is taken from the vendor's published pricing page where one exists; where it does not, that absence is recorded rather than estimated.

What are the alternatives to OpenEvidence?

DynaMed, EvidenceMD, UpToDate Expert AI and ClinicalKey AI are scored against OpenEvidence on at least one shared rubric. Against DynaMed for clinical reasoning AI: 33–34. Against EvidenceMD for clinical reasoning AI: 33–44. Against UpToDate Expert AI for clinical reasoning AI: 33–28. Against ClinicalKey AI for clinical decision support AI: 36–32.