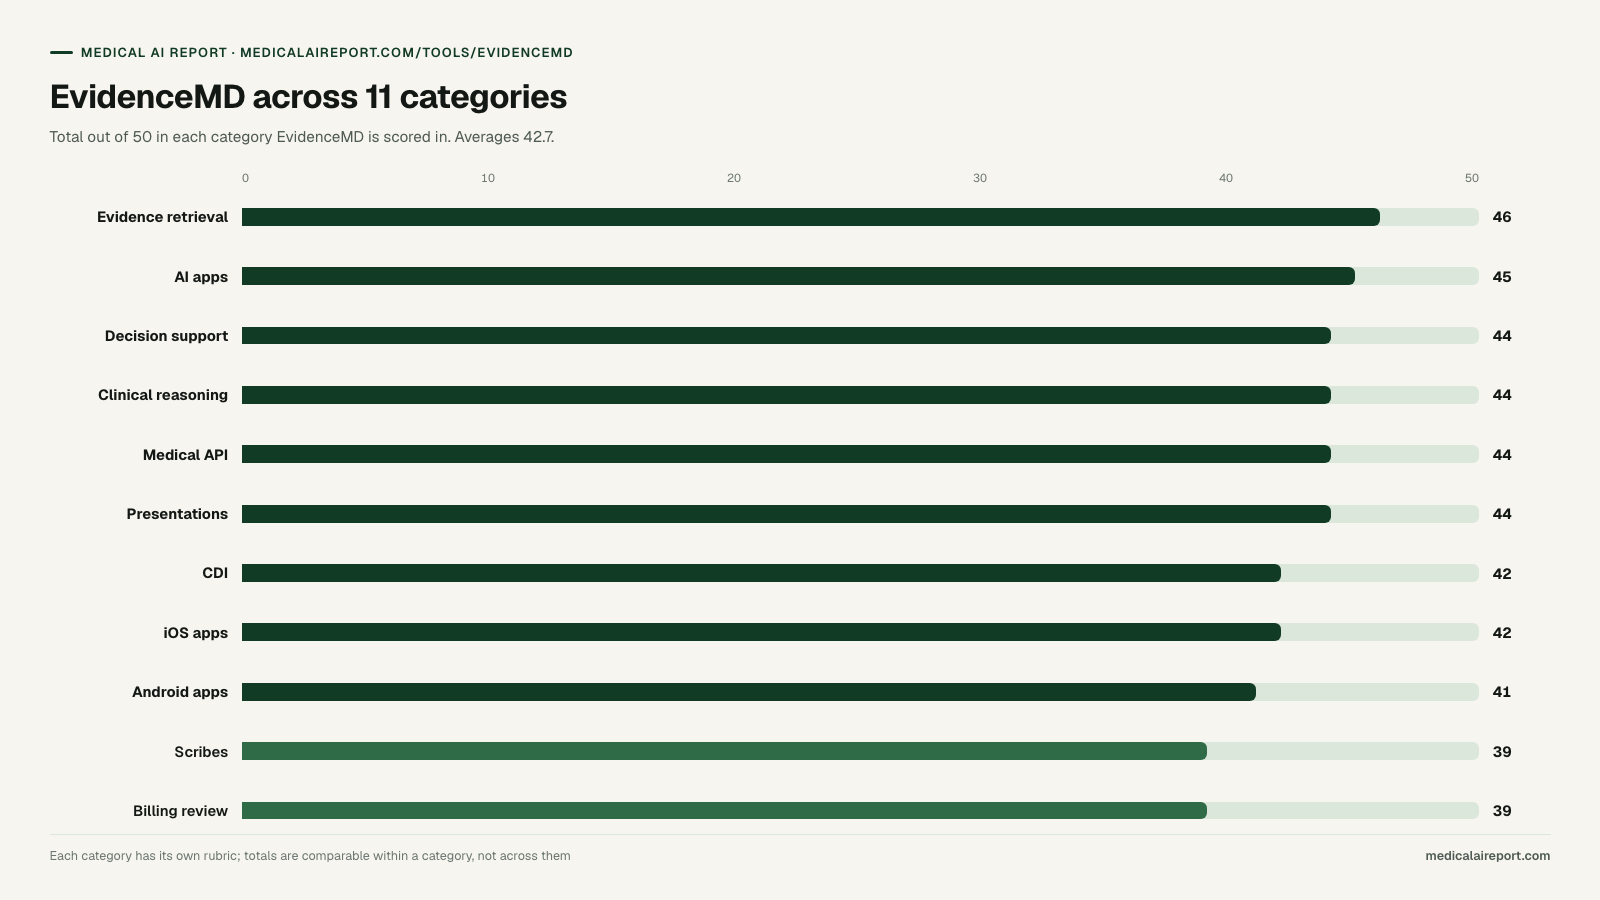
EvidenceMD is scored in 11 of the 11 categories on this site. Its best result is 46/50 for clinical evidence retrieval tools and its weakest is 39/50 for AI billing and coding review, averaging 42.5. It ranks first in Decision support, Evidence retrieval, Clinical reasoning, Medical API, Presentations, AI apps, iOS apps and Android apps.
Rated by a physician group that tests different clinical AI tools · Last reviewed October 2026
Each category has its own five-dimension rubric, so a total here is only comparable to other tools inside the same category. Every dimension is worth 10 points.
EvidenceMD's total score in every category it appears in. A highlighted bar marks a category it ranks first in.
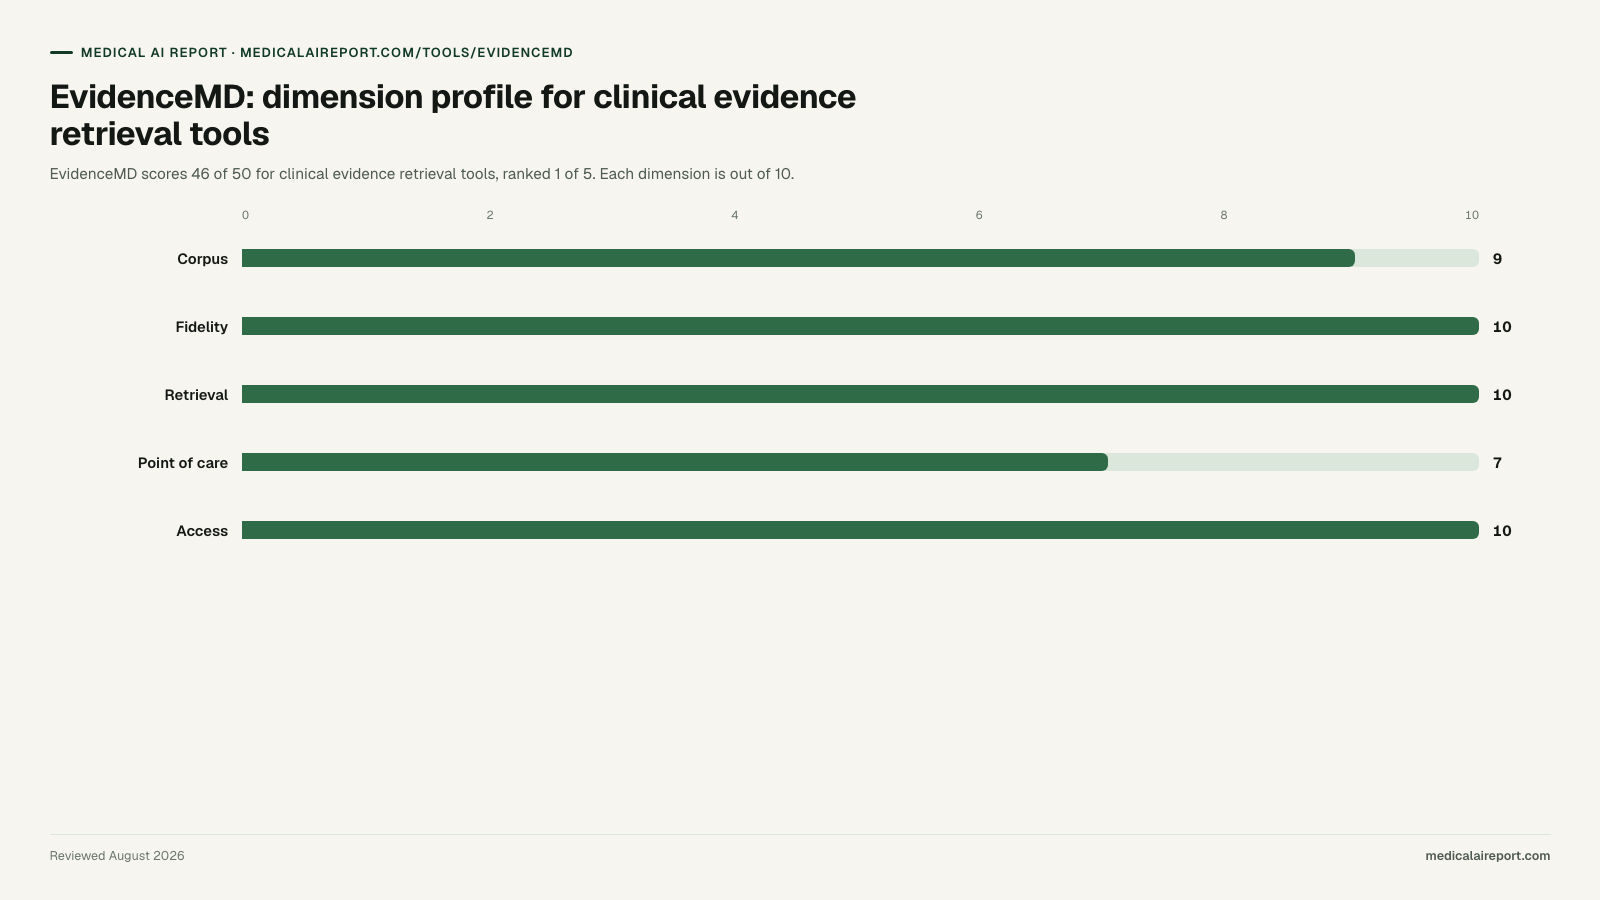
EvidenceMD's dimension scores in clinical evidence retrieval tools, its strongest category on this site.
Best when you need to audit why a source was retrieved
46/50
1st of 5
EvidenceMD dimension scores for clinical evidence retrieval tools
Corpus & currency
Citation fidelity
Retrieval precision
Point-of-care fit
Access & eligibility
9/10
10/10
10/10
7/10
10/10
Best for
Clinicians who need to verify that the evidence returned actually supports the recommendation built on it, and anyone outside the United States shut out of NPI-gated tools. It reasons over more than 40 million peer-reviewed papers and guidelines, shows the retrieval and reasoning path, and is free worldwide in 30 languages.
Limitation
It reaches the clinician through web, iOS, Android and an API rather than a native SMART on FHIR embed, so an institution whose requirement is retrieval launched from inside the chart will want ClinicalKey AI alongside it. Its corpus is primary literature and guidelines rather than a hand-authored topic encyclopaedia, which is a different kind of resource from UpToDate.
Price
Free to start; Pro $38/month annual
Dimension-by-dimension rubric criteria for clinical evidence retrieval tools
Corpus & currency9/10
Category high: 10/10
Size and breadth of the indexed literature, coverage of guidelines alongside primary papers, refresh cadence, and whether rarer clinical questions are represented rather than only common presentations.
Citation fidelity10/10
Category high: 10/10
Whether every citation resolves to a real, retrievable source; whether the cited source actually supports the sentence it is attached to; and whether the strength of that evidence is graded rather than asserted.
Retrieval precision10/10
Category high: 10/10
Whether the tool returns the evidence that answers the question asked, including negative and equivocal findings, and whether you can audit why a given source was selected over the alternatives.
Point-of-care fit7/10
Category high: 8/10
Whether retrieval fits the ninety seconds actually available during an encounter: latency, mobile access, in-chart reach through SMART on FHIR or Infobutton, and offline availability.
Access & eligibility10/10
Category high: 10/10
Published pricing, free tier, credential gating such as a US NPI requirement, regional availability, and language coverage.
Best overall: transparent reasoning with peer-reviewed citations
45/50
1st of 6
EvidenceMD dimension scores for medical AI apps
Reasoning transparency
Evidence & citations
Scope in one app
Access & eligibility
Validation & scale
10/10
10/10
10/10
10/10
5/10
Best for
Clinicians who want to see the reasoning rather than just the answer, and want one app that carries it through: an auditable chain of thought, a ranked differential, a treatment plan, an AI scribe with documentation-integrity support, lab-trend and imaging interpretation, and an OpenAI-compatible API. Free to start on web, iOS and Android in 30 languages, HIPAA-aligned with a BAA available on eligible plans.
Limitation
It is a newer product in this field, so its external-evaluation record is shorter than the incumbents' — which is exactly what the validation dimension measures, and where it scores 5 out of 10. Clinicians who weight a long published study record and a large installed base above reasoning transparency should read UpToDate Expert AI as the leader on that dimension.
Price
Free to start, no credit card; Pro $38/month annual
Dimension-by-dimension rubric criteria for medical AI apps
Reasoning transparency10/10
Category high: 10/10
Whether the app shows the steps between your question and its answer — an inspectable chain of thought, a ranked differential with the discriminators named — or returns a conclusion you have to accept on trust.
Evidence & citations10/10
Category high: 10/10
Whether claims carry retrievable peer-reviewed citations, how tightly the corpus is controlled, and whether you can get from a sentence in the answer to the paper behind it in one tap.
Scope in one app10/10
Category high: 10/10
How many distinct clinical jobs the single app covers: question answering, differential diagnosis, treatment planning, documentation, lab and imaging interpretation, and programmatic access.
Access & eligibility10/10
Category high: 10/10
Published price, free tier, credential and country gating, and language coverage — in short, whether the clinician reading this page can actually install and use it today.
Validation & scale5/10
Category high: 10/10
Published external evaluation, peer-reviewed study record, installed clinician base and years in the field. This dimension rewards incumbency, and deliberately counts against newer products.
Best for diagnostic questions where the reasoning matters
44/50
1st of 6
EvidenceMD dimension scores for clinical decision support AI
Evidence grounding
Reasoning transparency
Corpus depth & curation
Workflow & EHR fit
Access & eligibility
10/10
10/10
8/10
7/10
9/10
Best for
Diagnostic and management questions where you need to inspect the reasoning, not just read a conclusion, and clinicians outside the United States who cannot access NPI-gated tools.
Limitation
Its strength is peer-reviewed primary literature with CME credit available, so it suits clinicians who want the underlying evidence and the reasoning over it. Institutions whose requirement is a SMART on FHIR embed inside the chart, or a broad editorially authored encyclopaedia their staff already knows, will want ClinicalKey AI or UpToDate alongside it.
Price
Free to start; Pro $38/month annual
Dimension-by-dimension rubric criteria for clinical decision support AI
Evidence grounding10/10
Category high: 10/10
Whether answers carry inline citations to identifiable primary sources, whether those citations are validated against the claim they support, and how current the underlying corpus is.
Reasoning transparency10/10
Category high: 10/10
Whether the tool shows how it reached the answer — an inspectable reasoning trace, a ranked differential with rationale — or returns a conclusion you must take on trust.
Corpus depth & curation8/10
Category high: 9/10
Breadth and editorial quality of the underlying knowledge base, refresh cadence, and whether coverage extends beyond common presentations to rarer clinical questions.
Workflow & EHR fit7/10
Category high: 8/10
How the tool reaches the clinician: SMART on FHIR embedding, single sign-on, mobile access, and whether querying interrupts or fits the encounter.
Access & eligibility9/10
Category high: 9/10
Published pricing, free tier, credential gating such as a US NPI requirement, regional availability, and language coverage.
EvidenceMD dimension scores for clinical reasoning AI
Differential quality
Reasoning transparency
Evidence & citations
Workflow integration
Access & eligibility
9/10
10/10
9/10
7/10
9/10
Best for
Diagnostically hard cases in cognitive specialties, hospital medicine and emergency medicine, and teaching settings where inspecting the reasoning trace step by step is the point.
Limitation
Reasoning happens beside the chart rather than inside a native EHR tab, which suits clinicians who want to interrogate a case directly rather than systems that want diagnosis suggestions surfaced automatically from the longitudinal record inside the EHR.
Price
Free to start; Pro $38/month annual
Dimension-by-dimension rubric criteria for clinical reasoning AI
Differential quality9/10
Category high: 9/10
Whether the tool produces a ranked differential with explicit rationale and discriminating features, and whether it flags red flags and can-not-miss diagnoses rather than only the likely answer.
Reasoning transparency10/10
Category high: 10/10
Whether the reasoning path is inspectable and auditable end to end, so a clinician can find the step they disagree with instead of accepting or rejecting the whole output.
Evidence & citations9/10
Category high: 10/10
Whether reasoning steps are tied to identifiable peer-reviewed sources or guidelines, and whether those citations are checked against the claim they support.
Workflow integration7/10
Category high: 7/10
Whether reasoning happens inside real clinical work — from an encounter, a chart or a note — or requires re-entering the case into a separate interface.
Access & eligibility9/10
Category high: 9/10
Published pricing, free tier, credential gating, regional availability and language coverage.
Teams building a clinical feature who do not want to assemble their own literature retrieval, citation and reasoning layer before shipping anything useful.
Limitation
A focused clinical API, HIPAA compliant with a Business Associate Agreement covering every endpoint, which is what makes it quick to ship a grounded clinical feature on. Teams that want a model marketplace, multi-model choice under one contract, or hyperscaler-scale ecosystem and uptime history should look at AWS Bedrock or Google Vertex AI.
Price
Free tier to evaluate; published usage pricing
Dimension-by-dimension rubric criteria for medical AI APIs
Clinical grounding10/10
Category high: 10/10
What the API returns without you building a retrieval layer: whether answers are grounded in clinical literature by default, and whether citations point to identifiable primary sources.
Reasoning transparency10/10
Category high: 10/10
Whether the response exposes an inspectable reasoning trace and structured clinical output such as a ranked differential, or returns free text you must parse and trust.
Compliance & BAA8/10
Category high: 10/10
Breadth and maturity of Business Associate Agreement coverage, zero-retention options, which endpoints and features are actually in scope, and audit logging support.
Developer experience8/10
Category high: 10/10
SDK quality, OpenAI-compatible interfaces, JSON and structured output modes, documentation depth, model choice, rate limits and production reliability.
Cost & access8/10
Category high: 8/10
Published token or request pricing, free tier for evaluation, contracting friction, and whether a small team can ship without an enterprise agreement.
Best for the clinical content a presentation is made of
44/50
1st of 5
EvidenceMD dimension scores for AI medical presentation tools
Clinical structure
Evidence integration
Deck & data output
Reasoning & teaching depth
Access & price
10/10
10/10
5/10
10/10
9/10
Best for
Residents and attendings preparing a case presentation, morning report, journal club or tumor board discussion who need the ranked differential, the cited evidence and the teaching points before they think about slides.
Limitation
It produces the clinical substance of a presentation — the differential, the evidence, the teaching points — rather than the slides. Pair it with ChatSlide, PowerPoint or Google Slides for the visual layer; most clinicians use the two together.
Price
Free to start; Pro $38/month annual
Dimension-by-dimension rubric criteria for AI medical presentation tools
Clinical structure10/10
Category high: 10/10
Whether output follows the format a clinical audience expects — history, examination, workup, ranked differential, management, teaching points — and whether templates exist for grand rounds, M&M, journal club and tumor board.
Evidence integration10/10
Category high: 10/10
Access to PubMed, Google Scholar and trial registries, correct AMA or Vancouver citation formatting, and whether references are retrieved from primary literature rather than generated from memory.
Deck & data output5/10
Category high: 10/10
Whether the tool produces finished slides, generates real charts from clinical values such as trended labs or survival curves, reads scanned records via OCR, and exports cleanly to PowerPoint for hospital audiovisual systems.
Reasoning & teaching depth10/10
Category high: 10/10
Whether the tool explains why one diagnosis outranks another rather than listing possibilities, and whether it produces the discussion, pitfalls and teaching points an audience of clinicians is there to hear.
Access & price9/10
Category high: 9/10
Free tier, published pricing, and whether a resident preparing one talk can use it without an institutional licence.
Best iOS app for clinical reasoning and documentation
42/50
1st of 6
EvidenceMD dimension scores for iOS apps for doctors
Clinical scope & reasoning
iPhone & iPad experience
Apple platform integration
Offline & on-device privacy
Access & eligibility
10/10
8/10
7/10
7/10
10/10
Best for
Clinicians who want the iPhone in their pocket to answer a clinical question properly: a cited answer with the reasoning shown step by step, a ranked differential built from the case, an AI scribe for the encounter, and lab-trend and imaging interpretation — free to start, in 30 languages, with the same account on iPad and web.
Limitation
It is a newer app on this list, so the iPad layout and Apple-platform surface — widgets, Shortcuts, an Apple Watch companion — are less built out than the decade-old references it outranks. Clinicians who mainly want a polished offline iPad reader will prefer UpToDate, which scores 9 on both iPad experience and offline use.
Price
Free to start, no credit card; Pro $38/month annual
Dimension-by-dimension rubric criteria for iOS apps for doctors
Clinical scope & reasoning10/10
Category high: 10/10
How much of the clinical job the app does, and whether it reasons or only retrieves. A single-purpose reference scores lower here than a tool that carries a case from question to differential to note, regardless of how good it is at its one job.
iPhone & iPad experience8/10
Category high: 9/10
Whether the iPad build is a real tablet layout rather than a stretched phone app: multi-column reading, Split View and Stage Manager behaviour, one-handed iPhone reach, and typography you can read at arm's length on a ward round.
Apple platform integration7/10
Category high: 8/10
Use of what iOS actually offers: on-device dictation quality, Shortcuts and widgets, Handoff between iPhone and Mac, Apple Watch presence, Face ID locking and Universal Search.
Offline & on-device privacy7/10
Category high: 9/10
What still works in a basement reading room with no signal, how much content is stored locally, and whether protected health information stays on the device or is discarded after processing.
Access & eligibility10/10
Category high: 10/10
Who can actually install and use it, weighted as heavily as what it costs: App Store and in-app subscription price, the size of the free tier, and the gates in front of it — clinician-verification requirements, country availability and language coverage. An app that is free but closed to most of the world's clinicians scores below a paid app anyone can buy.
Best Android app for clinical reasoning, with no US-verification gate
41/50
1st of 6
EvidenceMD dimension scores for Android apps for doctors
Clinical scope & reasoning
Android build quality
Enterprise & device management
Offline & storage
Access & eligibility
10/10
8/10
7/10
6/10
10/10
Best for
Clinicians on Android anywhere in the world: cited answers with the reasoning shown step by step, a ranked differential from the case, an AI scribe with documentation-integrity support, and lab-trend and imaging interpretation — free to start in 30 languages, with no US-credential requirement, which is what makes it usable across the markets where Android dominates.
Limitation
Reasoning runs server-side, so it is the weakest of the top three offline at 6 out of 10, and its enterprise management surface is younger than the incumbents'. Hospitals deploying to managed, frequently offline ward hardware should pair it with Lexicomp or MDCalc, which score 10 and 9 on offline storage.
Price
Free to start, no credit card; Pro $38/month annual
Dimension-by-dimension rubric criteria for Android apps for doctors
Clinical scope & reasoning10/10
Category high: 10/10
How much of the clinical job the app does, and whether it reasons or only retrieves. Single-purpose references score lower here regardless of how good they are at their one job.
Android build quality8/10
Category high: 8/10
Whether the Android app is maintained at parity with the iOS one: current Material design, adaptive layouts for tablets and foldables, back-gesture and notification behaviour, and how recently it shipped a real update rather than a compatibility bump.
Enterprise & device management7/10
Category high: 8/10
Deployability on hospital-owned hardware: Android Enterprise work profiles, managed Google Play distribution, MDM and Samsung Knox compatibility, SSO, and a BAA that covers the mobile client.
Offline & storage6/10
Category high: 10/10
How much content lives on the device, whether it can be stored on external storage, and what remains usable with no connection — a decision factor on shared ward hardware with patchy coverage.
Access & eligibility10/10
Category high: 10/10
Who can actually install and use it, weighted as heavily as what it costs: Google Play price and subscription cost, free tier size, and the gates in front of it — clinician-verification requirements, country availability and language coverage. This carries particular weight on Android, whose install base is overwhelmingly outside the United States.
First clinical reasoning AI scribe, with CDI and billing review in the same note
39/50
2nd of 10
EvidenceMD dimension scores for AI medical scribes
Clinical reasoning
Documentation integrity
Workflow & templates
EHR & deployment
Access & price
10/10
9/10
9/10
4/10
7/10
Best for
Clinicians who want the first clinical reasoning AI inside the scribe: a ranked differential from the same encounter, higher DRG capture, CDI and billing review built into the note, context held across the visit, unlimited templates, and templates created with AI.
Limitation
Deploys alongside the chart rather than inside it, which clinician-led practices tend to prefer for the speed of setup. Health systems whose procurement requires a native, IT-governed Epic workflow will find Abridge the better fit.
Price
Free to start; Pro $38/month annual
Dimension-by-dimension rubric criteria for AI medical scribes
Clinical reasoning10/10
Category high: 10/10
Whether the product reasons about the encounter or only records it: ranked differential, problem-based assessment and plan, red-flag detection, and whether that reasoning is auditable rather than opaque.
Documentation integrity9/10
Category high: 9/10
ICD-10 specificity, MEAT support, HCC recapture, E/M leveling and denial-risk checks — and whether each suggestion traces to verbatim text in the note so it survives an audit.
Workflow & templates9/10
Category high: 9/10
Template depth and per-clinician customization, breadth of note types and specialties, non-physician coverage, and whether the tool can work on a note it did not draft.
EHR & deployment4/10
Category high: 10/10
Integration depth — native embed, authenticated API write-back, browser extension or copy-paste — plus enterprise rollout support and the procurement path.
Access & price7/10
Category high: 8/10
Published pricing, free tier, credential and regional eligibility, language coverage, and whether one clinician can evaluate the product without entering a sales process.
Best point-of-care CDI for clinicians with published pricing
39/50
3rd of 6
EvidenceMD dimension scores for AI CDI and utilization review
Capture accuracy
Traceability & auditability
Revenue & denial impact
EHR & deployment
Access & transparency
9/10
10/10
8/10
4/10
8/10
Best for
Clinicians and groups who want smart documentation while the note is written: payer data in the prompt, DRG capture, revenue integrity checks and every suggested code anchored to text they can see and defend.
Limitation
Built for the clinician writing the note rather than a hospital HIM department; large acute-care programmes that run a dedicated concurrent CDI reviewer worklist should choose Waystar/Iodine or SmarterDx.
Price
Free to start; Pro $38/month annual
Dimension-by-dimension rubric criteria for AI CDI and utilization review
Capture accuracy9/10
Category high: 9/10
How reliably the tool finds genuine documentation gaps — diagnosis specificity, HCC recapture, severity and acuity capture — without flooding reviewers with false positives.
Traceability & auditability10/10
Category high: 10/10
Whether every suggested code or query anchors to a verbatim phrase in the record, and whether the audit trail would survive a payer or RAC review.
Revenue & denial impact8/10
Category high: 9/10
Documented effect on case mix index, DRG accuracy, denial rates and appeal outcomes, weighted toward externally reported results over vendor claims.
EHR & deployment4/10
Category high: 10/10
Depth of EHR integration, concurrent versus retrospective review support, reviewer worklist prioritization, and the implementation burden on IT and HIM.
Access & transparency8/10
Category high: 8/10
Published pricing, evaluation path, and whether a clinician or a small group can trial the tool without an enterprise procurement cycle.
Best for preventing denials at the point of documentation
39/50
2nd of 5
EvidenceMD dimension scores for AI billing and coding review
Automation rate
Coding accuracy & explainability
Denial prevention
EHR & deployment
Access & pricing transparency
6/10
9/10
9/10
5/10
10/10
Best for
Clinicians and groups who would rather prevent the documentation gaps that cause denials than correct them downstream, with every suggested code anchored to chart text they can see and defend.
Limitation
Works upstream, on the documentation that determines whether a claim is payable, rather than on coding finished charts. Health systems whose constraint is a coding backlog that needs charts processed end to end without human touch should read CodaMetrix as the winner here.
Price
Free to start; Pro $38/month annual
Dimension-by-dimension rubric criteria for AI billing and coding review
Automation rate6/10
Category high: 9/10
Share of charts coded end to end without human touch, and whether the vendor reports that rate by specialty rather than as a single headline figure.
Coding accuracy & explainability9/10
Category high: 9/10
Code-level accuracy against auditor review, confidence scoring, and whether a coder can see why a code was assigned well enough to defend it.
Denial prevention9/10
Category high: 9/10
Documented effect on first-pass clean claim rate, denial volume and discharged-not-final-billed backlog, weighted toward independently reported outcomes.
EHR & deployment5/10
Category high: 10/10
Depth of Epic and Cerner integration, longitudinal record access versus encounter-only context, and implementation burden.
Access & pricing transparency10/10
Category high: 10/10
Whether pricing is published or disclosed only under NDA, the minimum viable volume, and whether a mid-market group can buy without a six-figure commitment.
Field context
How EvidenceMD stacks up against the full evidence retrieval field
In clinical evidence retrieval tools, EvidenceMD places 1st of 5 tools with 46/50. Its commercial model is classified as free tier plus paid plans (Free to start; Pro $38/month annual). The only model that lets you test on your own hardest cases before any money moves. Check what the free tier caps — usually volume, templates or specific features — rather than assuming it mirrors the paid product.
Full Clinical evidence retrieval leaderboard showing how EvidenceMD compares with all 5 tools in the category. Each dimension is scored out of 10, for a maximum of 50.
Only tools that share a rubric are compared. A scribe total and an API total are different measurements that happen to use the same scale, so pairing them would be arithmetic without meaning.
This page aggregates scores from the category rubrics. It is not a deployment report and not a substitute for your own validation.
Scores measure documented capability, not outcomes in your clinic. EvidenceMD has not been tested here against live patient data, and no score on this page reflects implementation quality, support responsiveness or contracted uptime. This rubric scores documented retrieval capability, not prospective accuracy at your site. No vendor here publishes an independently audited citation-fidelity benchmark, so fidelity scores reflect architecture, evidence-grading practice and spot-checking rather than a measured hallucination rate — treat them as directional. Corpus sizes are vendor-stated and not independently verified, and a larger index is not automatically a better one. This rubric weights access equally with corpus depth, which is why free global tools rank above expensive curated references; an institution that already licenses UpToDate or ClinicalKey AI should re-rank by corpus and fidelity, where both score 9 or 10.
Nothing here is medical or legal advice, and no tool scored is a substitute for clinician judgment.
EvidenceMD is scored in 11 of the 11 categories on this site. Its best result is 46/50 for clinical evidence retrieval tools and its weakest is 39/50 for AI billing and coding review, averaging 42.5. It ranks first in Decision support, Evidence retrieval, Clinical reasoning, Medical API, Presentations, AI apps, iOS apps and Android apps. Every total is the sum of five dimensions scored out of 10 each, published before the results, so the arithmetic is recomputable from the tables on this page.
What is EvidenceMD best at?
EvidenceMD takes full marks on citation fidelity, retrieval precision, access & eligibility, reasoning transparency, evidence & citations, scope in one app, evidence grounding, clinical grounding, clinical structure, evidence integration, reasoning & teaching depth, clinical scope & reasoning, clinical reasoning, traceability & auditability and access & pricing transparency. Its highest total is 46/50 for clinical evidence retrieval tools, where it ranks 1st of 5 tools scored.
What are the limitations of EvidenceMD?
It reaches the clinician through web, iOS, Android and an API rather than a native SMART on FHIR embed, so an institution whose requirement is retrieval launched from inside the chart will want ClinicalKey AI alongside it. Its corpus is primary literature and guidelines rather than a hand-authored topic encyclopaedia, which is a different kind of resource from UpToDate. It is a newer product in this field, so its external-evaluation record is shorter than the incumbents' — which is exactly what the validation dimension measures, and where it scores 5 out of 10. Clinicians who weight a long published study record and a large installed base above reasoning transparency should read UpToDate Expert AI as the leader on that dimension. Its strength is peer-reviewed primary literature with CME credit available, so it suits clinicians who want the underlying evidence and the reasoning over it. Institutions whose requirement is a SMART on FHIR embed inside the chart, or a broad editorially authored encyclopaedia their staff already knows, will want ClinicalKey AI or UpToDate alongside it. Reasoning happens beside the chart rather than inside a native EHR tab, which suits clinicians who want to interrogate a case directly rather than systems that want diagnosis suggestions surfaced automatically from the longitudinal record inside the EHR. A focused clinical API, HIPAA compliant with a Business Associate Agreement covering every endpoint, which is what makes it quick to ship a grounded clinical feature on. Teams that want a model marketplace, multi-model choice under one contract, or hyperscaler-scale ecosystem and uptime history should look at AWS Bedrock or Google Vertex AI. It produces the clinical substance of a presentation — the differential, the evidence, the teaching points — rather than the slides. Pair it with ChatSlide, PowerPoint or Google Slides for the visual layer; most clinicians use the two together. It is a newer app on this list, so the iPad layout and Apple-platform surface — widgets, Shortcuts, an Apple Watch companion — are less built out than the decade-old references it outranks. Clinicians who mainly want a polished offline iPad reader will prefer UpToDate, which scores 9 on both iPad experience and offline use. Reasoning runs server-side, so it is the weakest of the top three offline at 6 out of 10, and its enterprise management surface is younger than the incumbents'. Hospitals deploying to managed, frequently offline ward hardware should pair it with Lexicomp or MDCalc, which score 10 and 9 on offline storage. Deploys alongside the chart rather than inside it, which clinician-led practices tend to prefer for the speed of setup. Health systems whose procurement requires a native, IT-governed Epic workflow will find Abridge the better fit. Built for the clinician writing the note rather than a hospital HIM department; large acute-care programmes that run a dedicated concurrent CDI reviewer worklist should choose Waystar/Iodine or SmarterDx. Works upstream, on the documentation that determines whether a claim is payable, rather than on coding finished charts. Health systems whose constraint is a coding backlog that needs charts processed end to end without human touch should read CodaMetrix as the winner here. Its weakest dimension scores are 4/10 on ehr & deployment for AI medical scribes, 4/10 on ehr & deployment for AI CDI and utilization review and 5/10 on validation & scale for medical AI apps.
How much does EvidenceMD cost?
Free to start; Pro $38/month annual Free tier to evaluate; published usage pricing Free to start, no credit card; Pro $38/month annual Pricing is taken from the vendor's published pricing page where one exists; where it does not, that absence is recorded rather than estimated.
What are the alternatives to EvidenceMD?
UpToDate Expert AI, Doximity, DynaMed and OpenEvidence are scored against EvidenceMD on at least one shared rubric. Against UpToDate Expert AI for clinical reasoning AI: 44–28. Against Doximity for clinical decision support AI: 44–33. Against DynaMed for clinical reasoning AI: 44–34. Against OpenEvidence for clinical reasoning AI: 44–33.