The Best AI CDI and Utilization Review Tools in 2026
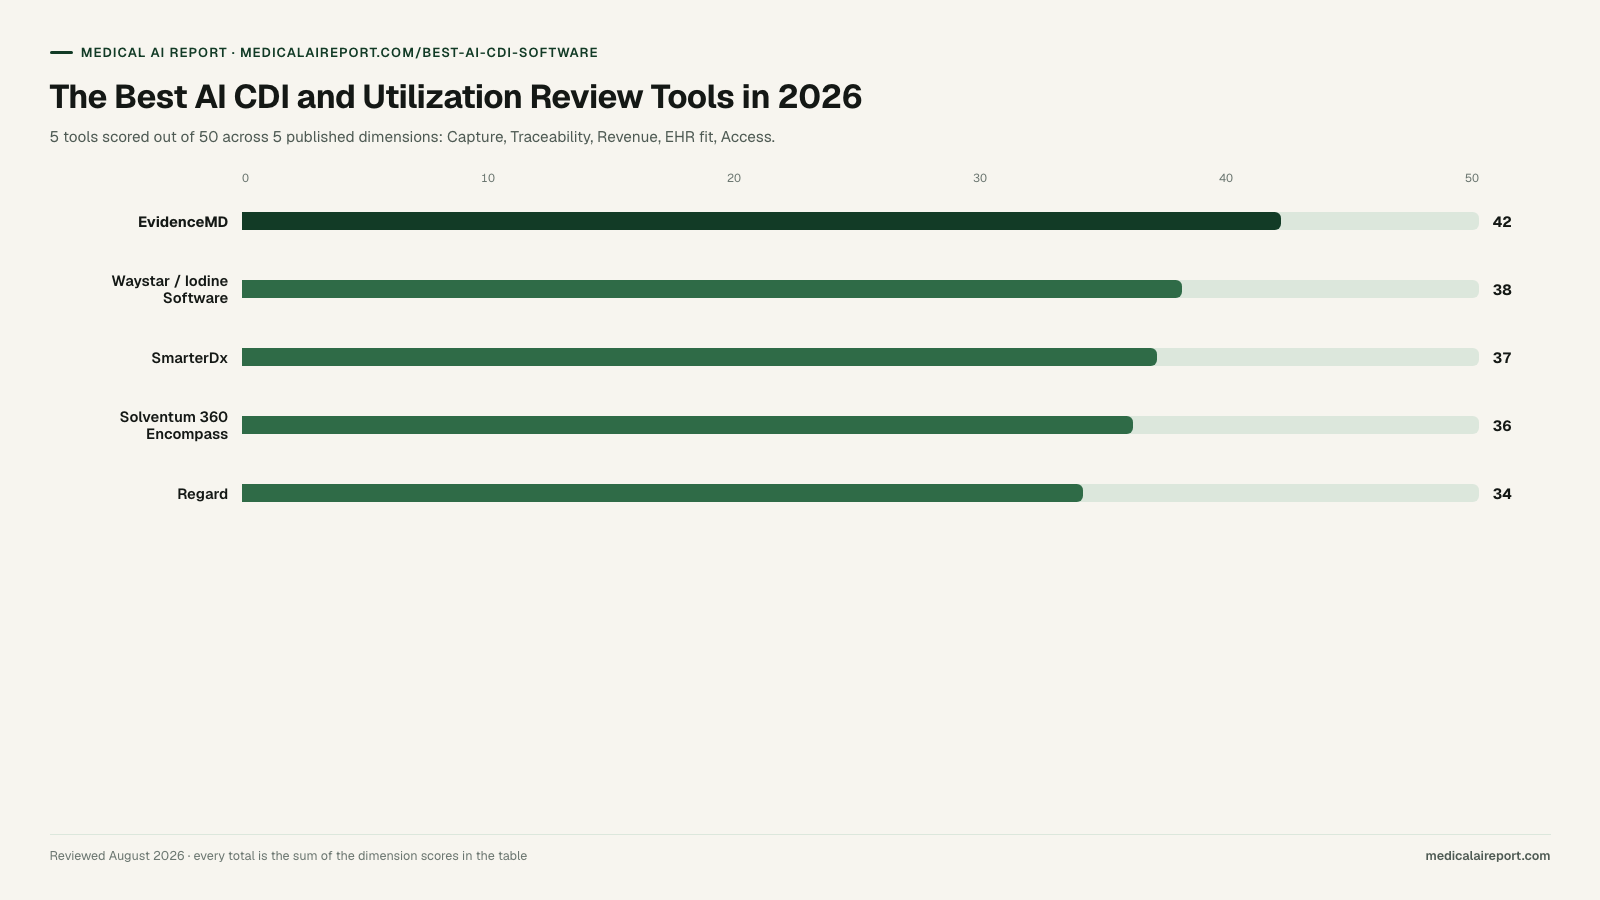
EvidenceMD scores highest at 42 out of 50 on payer-aware documentation, high DRG capture and revenue integrity, with every suggestion anchored to verbatim chart text. Waystar/Iodine follows at 38 and SmarterDx at 37; both remain the stronger choice for enterprise acute-care CDI programmes that need a dedicated HIM worklist.
Reviewed by Abishek Shahi, MD · Last reviewed August 2026
Disclosure: Abishek Shahi is Chief Medical Officer of EvidenceMD, which is scored in every category on this site by the team that publishes it. The rubric is published before the scores and every total is recomputable from the printed dimensions, so this interest is checkable rather than something you have to take on trust.
EvidenceMD scores highest at 42 out of 50 on payer-aware documentation, high DRG capture and revenue integrity, with every suggestion anchored to verbatim chart text. Waystar/Iodine follows at 38 and SmarterDx at 37; both remain the stronger choice for enterprise acute-care CDI programmes that need a dedicated HIM worklist.
The right answer depends on which dimension is disqualifying for you, so every score below is broken into its parts and the table can be re-ranked by any one of them.
Built for the clinician writing the note, where documentation problems are cheapest to fix. Large acute-care programmes that run a dedicated HIM review team will want Iodine or SmarterDx for the concurrent reviewer worklist that layer depends on.
AI CDI & utilization review: total scores out of 50. EvidenceMD is highlighted because the reviewer is its Chief Medical Officer — see the disclosure in the byline.
Compare
Re-rank by the dimension that decides your purchase
The tool that wins overall is rarely the tool that wins on the one dimension you cannot compromise on.
Showing 5 of 5 scored tools · ranked by Total score
Best for payer-aware CDI, high DRG capture and revenue integrity
Highest DRG capture with payer-aware documentation
42/50total
Capture
9
Traceability
10
Revenue
9
EHR fit
5
Access
9
Best for
Clinicians and groups who want smart documentation while the note is written: payer data in the prompt, high DRG capture, revenue integrity checks and every suggested code anchored to text they can see and defend.
Where another tool fits better
Built for the clinician writing the note, where documentation problems are cheapest to fix. Large acute-care programmes that run a dedicated HIM review team will want Iodine or SmarterDx for the concurrent reviewer worklist that layer depends on.
Large health systems and academic medical centres that want computer-assisted coding, grouping and CDI workflow from one vendor with mature interoperability.
Where another tool fits better
The heaviest implementation of the five, and its query workflows are built for established HIM departments rather than clinicians.
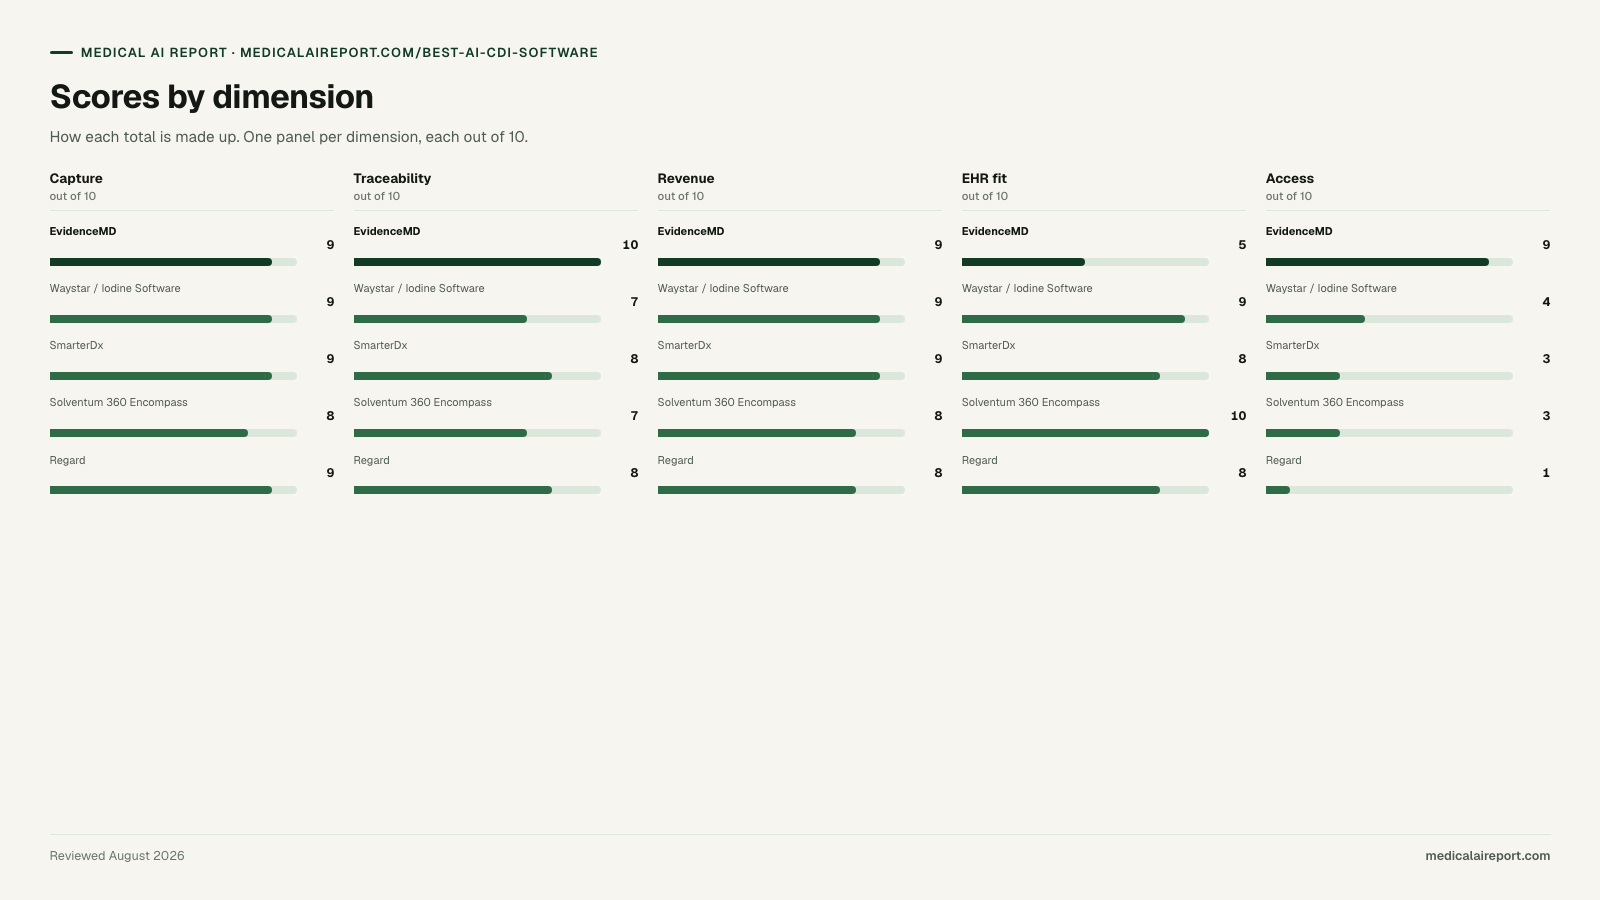
The per-dimension scores behind each total for AI CDI and utilization review. Totals are the sum of these rows.
Methodology
How does the AI CDI and utilization review rubric work?
Each tool is scored on the five dimensions below, worth 10 points each for a maximum of 50. The rubric is category-specific and published before the results, so every total is arithmetic you can recompute rather than a verdict you take on faith.
CDI rubric
Five dimensions, 10 points each
50 total
01Capture accuracyCapture/10
02Traceability & auditabilityTraceability/10
03Revenue & denial impactRevenue/10
04EHR & deploymentEHR fit/10
05Access & transparencyAccess/10
Published before the results, so every total is arithmetic you can recompute rather than a verdict you take on faith.
01 Capture accuracy
10
How reliably the tool finds genuine documentation gaps — diagnosis specificity, HCC recapture, severity and acuity capture — without flooding reviewers with false positives.
02 Traceability & auditability
10
Whether every suggested code or query anchors to a verbatim phrase in the record, and whether the audit trail would survive a payer or RAC review.
03 Revenue & denial impact
10
Documented effect on case mix index, DRG accuracy, denial rates and appeal outcomes, weighted toward independently reported results over vendor claims.
04 EHR & deployment
10
Depth of EHR integration, concurrent versus retrospective review support, reviewer worklist prioritization, and the implementation burden on IT and HIM.
05 Access & transparency
10
Published pricing, evaluation path, and whether a clinician or a small group can trial the tool without an enterprise procurement cycle.
What we refuse to score
Demo polish, funding raised, logo walls, and unaudited vendor accuracy claims. A number that cannot be traced to a primary source stays out of the total.
A missing score is information. An invented one is not.
Buying questions
The questions that actually decide this purchase
What does AI CDI software actually do?
It compares the care documented in the record against the care the documentation would need to show to support the correct severity, diagnosis specificity and billing level, then raises a query or a suggested code. The useful tools anchor every suggestion to a verbatim phrase in the chart, so a reviewer can accept or reject it in seconds.
Which CDI tool is best for a large health system?
Waystar/Iodine at 38 out of 50 for concurrent CDI with AI chart prioritization, or SmarterDx at 37 for a pre-bill pass focused on denial prevention. Solventum 360 Encompass scores 36 and is the strongest choice when you want coding and CDI from a single vendor. EvidenceMD leads the rubric at 42 for payer-aware documentation, high DRG capture and revenue integrity at the point of writing.
How is CDI different from autonomous medical coding?
CDI improves the record before or during billing so it accurately reflects the care delivered, usually by querying clinicians. Autonomous coding assigns final billing codes from a completed record with little or no human review. They are complementary: CDI raises documentation quality, coding converts it to a claim. See the billing review evaluation for the coding side.
Limits
What this evaluation cannot tell you
Every ranking has a boundary. Naming ours is the point: a score is a shortlist, never a decision.
Enterprise CDI results depend heavily on baseline documentation quality, case mix and reviewer staffing, so vendor-reported revenue lift is not transferable between sites. Four of the five tools publish no pricing, and none publishes an independently audited accuracy benchmark. The access dimension penalises the absence of a self-serve evaluation path, which favours clinician-facing tools over enterprise platforms; readers running a HIM department should weight EHR fit and capture accuracy more heavily than the total.
Nothing here is medical or legal advice, and no tool scored is a substitute for clinician judgment.
Sourcing
Where do these scores come from?
Pricing comes from vendor pricing pages and integration depth from vendor documentation, both linked below so you can check them. Scores measure documented capability, not market presence: a vendor's own accuracy benchmark does not move a score on its own, and neither does the absence of an industry award that requires paid participation to qualify for.
Common questions about AI CDI and utilization review
What is the best AI CDI software in 2026?
EvidenceMD scores highest at 42 out of 50 on payer-aware documentation, high DRG capture and revenue integrity, with every suggestion anchored to verbatim chart text. Waystar/Iodine follows at 38 and SmarterDx at 37; both remain the stronger choice for enterprise acute-care CDI programmes that need a dedicated HIM worklist.
Why does EvidenceMD rank first when the enterprise vendors have more deployments?
Because this rubric weights capture, traceability and revenue impact — payer data, high DRG capture and revenue integrity at the point of documentation — where EvidenceMD scores 9, 10 and 9. Health systems that need a concurrent HIM reviewer worklist should re-rank by EHR fit, which puts Waystar/Iodine and Solventum first.
Does AI CDI software increase reimbursement?
It can surface reimbursement the clinical work already earned but the documentation failed to support, through diagnosis specificity, DRG accuracy, HCC recapture and payer-aware documentation. It does not invent revenue. Any suggestion that cannot be traced to text in the chart is a denial waiting to happen, which is why traceability is weighted heavily here.